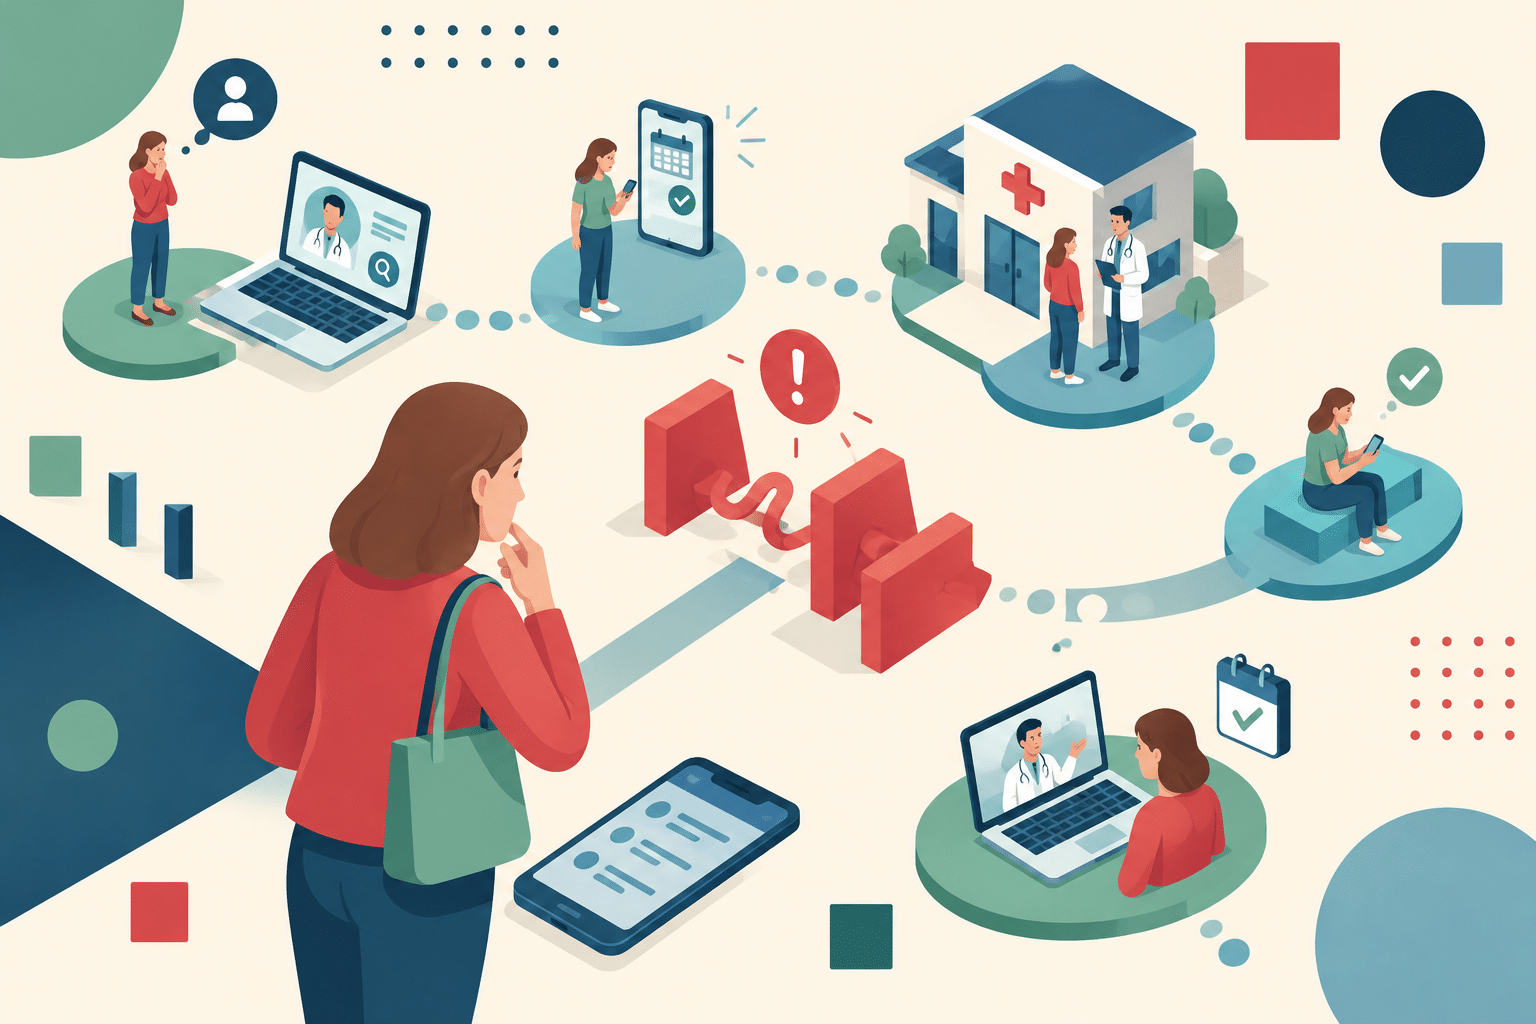

Find the Friction in Your Patient Journey by looking at care through the eyes of the person trying to get it, not only through the systems designed to deliver it. A patient may discover your practice through a search, call for an appointment, complete forms, travel to a clinic, meet a clinician, and wait for next steps. Each handoff can feel small to the organization, yet the accumulated effort can determine whether the patient follows through. Patient friction is any avoidable effort, uncertainty, delay, or obstacle that makes the next step harder than it needs to be.
Friction does not always look like a formal complaint. It can appear as a patient who gives up halfway through online scheduling, a caller who repeats the same information to several people, or a missed visit after unclear preparation instructions. It may also show up in staff workarounds, repeated callbacks, incomplete referrals, and appointment slots that remain unused despite demand. These signals matter because they connect patient experience with operational performance. When people cannot navigate the process, access, capacity, continuity, and trust can all suffer.
The goal is not to make every interaction frictionless in an absolute sense. Healthcare includes necessary clinical safeguards, complex decisions, and moments of discomfort that cannot be removed by better wording. The practical goal is to distinguish necessary effort from avoidable effort, then reduce the avoidable parts without weakening safety or care quality. A well-run review gives teams a shared view of what patients encounter, where the process breaks down, and which improvements are most likely to help.
A patient journey can span months or years, so a team needs a clear boundary before mapping it. Start with a specific patient goal, such as finding a primary care appointment, completing a diagnostic test, or understanding a new referral. Then choose a beginning and an ending that are meaningful to both the patient and the organization. For an access review, the journey might begin when someone recognizes a need for care and end when they know what happens after the visit. A tight boundary makes the work achievable and helps the group avoid trying to fix every process at once.
Define whose journey you are studying as carefully as you define the steps. A new patient with limited English proficiency may face different obstacles from an established patient who uses a portal regularly. A caregiver booking on behalf of a family member may need clear authorization guidance, while a patient with mobility needs may be focused on transportation and building access. Select one priority audience and one real-world situation for the first map. This does not mean other people matter less; it means the team can notice meaningful differences instead of flattening them into an imaginary average patient.
Agree on what the journey includes and what it does not include. If the focus is scheduling, decide whether the review covers search, phone access, online booking, insurance questions, reminders, and cancellation or rescheduling. Write down assumptions that could otherwise derail discussion, including the clinics, appointment types, languages, and channels involved. Ask a front-desk colleague and a patient-facing team member to check whether the boundary reflects reality. A short, specific scope is more useful than a large map that cannot be validated or acted upon.
Begin with evidence already available inside the organization. Review call reasons, abandoned calls, portal search terms, scheduling completion, referral aging, no-show rates, complaint themes, and repeated questions to staff. Compare the numbers by channel, clinic, appointment type, and relevant patient group when privacy rules and sample sizes allow. These data points can reveal where to investigate, but they do not explain what a patient was trying to do or why a step felt difficult. Treat operational data as a set of clues, not as a complete account of the patient experience.
Pair the numbers with patient and staff accounts. Short interviews can ask what the person was trying to accomplish, what happened next, what felt confusing, and what they did when the process stalled. Invite patients who completed the journey as well as people who postponed, switched channels, or did not finish, because relying only on successful visits creates a misleading picture. Staff can describe the workarounds that keep the process moving, such as manually correcting a form or calling another department to confirm a referral. These conversations should be respectful, voluntary, and designed to learn rather than defend a process.
Make participation easy and accessible. Offer more than one way to share feedback, use plain language, consider interpretation needs, and avoid asking people to retell sensitive details that are not relevant to the question. Keep notes focused on actions, barriers, and outcomes rather than personal judgments. If the team cannot speak directly with patients, make that limitation visible and use a mix of feedback channels, advisory input, and observed service interactions. A map built from incomplete evidence can still be useful, but clearly labeling what is known and what is assumed prevents guesses from hardening into facts.
Lay out the journey in the order a patient experiences it, rather than in the order departments are organized. A simple map may include awareness, choosing a provider, requesting an appointment, preparing for the visit, arriving, receiving care, and understanding follow-up. Under each stage, record the patient’s goal, the actions they take, the channel they use, and the people or systems they encounter. A step such as “schedule appointment” may actually involve searching for a phone number, waiting on hold, explaining the reason for the visit, checking availability, and receiving confirmation. Breaking broad labels into observable actions helps expose the effort hidden inside familiar processes.
Add the patient’s questions, expectations, and emotional context alongside those actions. Someone seeking a specialist may be worried about symptoms and unsure whether a referral has been received. Someone arranging a routine visit may simply want to know how soon an appointment is available and whether the clinic accepts their coverage. Do not assume that every stage is positive or negative; capture the emotions patients describe and the uncertainty they report. The map should show what happens, what the person needs at that moment, and where the experience changes direction.
Use a format the team can revise together, whether that is a shared document, a wall map, or a digital board. Mark the source of each insight, such as interview, call data, observation, or staff report, and distinguish confirmed evidence from hypotheses. Include handoffs and wait states because friction often lives between teams rather than inside a single interaction. Invite representatives from scheduling, clinical operations, communications, billing, and patient support to review the map, but keep the patient’s task at its center. A useful patient journey map is not a polished poster; it is a working model the team can challenge and improve.
Look for points where the patient must repeat information, guess what to do, switch channels, or wait without knowing why. A form that asks for details already provided by phone is a repetition signal. A voicemail that promises a callback without a timeframe creates uncertainty, while a referral that sits between departments can leave a patient unsure whether anyone is taking responsibility. These are observable moments, not abstract impressions. For each one, describe the friction in plain terms: who is affected, what they are trying to do, what blocks progress, and what happens as a result.
Check for effort that has been transferred rather than removed. An organization may reduce staff workload by directing everyone to a portal, but the patient may not have reliable internet, may be unable to create an account, or may not understand which option to select. A process can look efficient in a dashboard while creating extra calls, late arrivals, or incomplete information elsewhere. Ask what a patient must know, provide, remember, or coordinate to finish each step. The more the process depends on a patient to connect disconnected systems, the more likely it is that avoidable friction is hiding in the journey.
Notice barriers that affect some patients more than others. Language access, disability, transportation, work schedules, caregiving responsibilities, digital access, and financial concerns can all change how a step works in practice. Compare journeys where appropriate, but do not treat demographic categories as explanations by themselves; ask about the actual circumstances and obstacles people encounter. A longer wait may be especially difficult when instructions are unclear or rescheduling options are limited. Mapping differences makes it possible to improve access without assuming that one standard pathway serves everyone equally well.
Once the map contains a range of friction points, resist the urge to fix everything at once. Prioritize issues by considering how many people encounter them, how severe the consequence is, how much control your team has, and how quickly you can test a change. A small obstacle repeated across thousands of patients may deserve attention before a rare inconvenience, while a less common barrier may still be urgent if it creates a safety or access risk. Include equity and patient effort in the discussion so that easy-to-measure issues do not automatically outrank important but less visible needs. The aim is a transparent choice, not a falsely precise score.
Use a quick checklist to make that choice consistent. Ask whether the issue blocks access or delays care, how often it appears in patient or operational evidence, which groups bear the greatest burden, and whether it leads to avoidable calls, rework, missed appointments, or confusion. Then ask whether the cause is within the team’s control, what a low-risk first test could be, and what measure would show improvement. Score each question simply as low, medium, or high, and record the reasoning in a sentence. A shared checklist makes tradeoffs visible and helps teams revisit priorities when new evidence arrives.
After scoring, select one or two high-value friction points rather than building a long wish list. Write a problem statement that describes the patient, the moment, and the obstacle without slipping into a solution too early. For example, “New patients calling for a first appointment do not know which information to prepare, so calls take longer and some callers abandon the process” is more useful than “We need a new website.” The wording should be specific enough to guide a test but open enough to allow different solutions. Bring the selected problem back to patients or frontline staff to confirm that it reflects the experience they described.
A patient journey review creates value when it leads to a change someone can observe. The first improvement does not need to involve new software, a large budget, or a complete redesign. It might be a clearer appointment message, a simpler handoff, a better callback expectation, or a small adjustment to the information patients receive before a visit. Choose an intervention that addresses the cause you identified, not only the symptom that is easiest to see. Keep the test narrow enough that the team can learn from it within a week or two.
Use the workflow below to move from evidence to an initial test this week. Assign one owner to coordinate the work and invite the people who perform or receive the affected steps. Before making a change, check clinical, privacy, accessibility, and operational requirements so that the test remains safe and appropriate. Decide how you will compare results and how you will capture unexpected effects. A small test is not permission to ignore governance; it is a disciplined way to learn before investing in a broader rollout.
For example, a clinic that hears repeated questions about what to bring to a first appointment could test a plain-language preparation message with one appointment type. Staff can track related inbound calls, incomplete check-ins, and patient comments before and during the test. The team should not claim success merely because the message was sent; it should check whether people understood it and whether staff workload shifted elsewhere. At the end of the week, decide what the evidence supports and document the next experiment. This rhythm makes improvement part of normal operations rather than a one-time mapping exercise.
Mini case note: appointment access. Imagine a community practice where patients say that reaching the right person takes too long. Call data show frequent transfers and a cluster of abandoned calls during the lunch hour, while staff report that callers often do not know whether they need a new-patient visit or a follow-up. The map reveals that the phone menu asks patients to choose a category they cannot confidently identify, then routes some callers to a team that cannot book the requested appointment. The friction is not simply “phone access”; it is the combination of unclear choices and a handoff that does not resolve the patient’s task.
The practice tests a clearer phone option for appointment requests and gives the receiving team a short decision guide for common visit types. It also tells callers what to expect if a live answer is not available, including when they should expect a response and what information to leave. During the test, the team checks abandoned calls, transfers, callback completion, and staff feedback rather than focusing on call volume alone. If the revised menu reduces transfers but increases unresolved callbacks, the team has learned that routing improved while follow-through still needs work. The next action should respond to that evidence, not declare the entire access problem solved.
Mini case note: referral follow-through. In an anonymized specialty clinic, patients and primary care staff both report uncertainty after referrals are sent. The administrative dashboard shows that many referrals are eventually processed, but the time between receipt, review, and patient contact varies widely. A journey map highlights a quiet gap: the referring office assumes the specialty clinic will contact the patient, while the specialty clinic is waiting for missing information and the patient does not know the referral is incomplete. The patient is left to coordinate an invisible handoff among organizations.
The clinic tests a referral status message for a limited group, using clear language to explain what has been received, what is still needed, and who to contact with questions. Staff also use a simple tracking field to distinguish pending clinical review from incomplete paperwork. The team monitors time to first contact, referrals returned for missing information, patient inquiries about status, and staff workload. A status message alone may not fix delays caused by clinical capacity, but it can reduce uncertainty and reveal where the process truly stalls. The example shows why a journey map should connect the patient’s understanding with the operational step behind it.
Choose measures that reflect the problem you are trying to solve. For an appointment access test, useful indicators might include time from request to booked appointment, call abandonment, scheduling completion, transfer rate, or the percentage of patients who receive a callback within the promised window. For a referral journey, consider time to first contact, the share of referrals missing required information, time spent in each status, and patient contacts asking for an update. The right KPI depends on the friction point, so avoid importing a dashboard metric simply because it is already available. A measure should help the team make a decision.
Pair operational indicators with patient-reported feedback. A shorter call may be a positive signal, but it does not prove that the caller understood the next step. A quick survey, a brief follow-up question, or structured comments gathered through existing channels can help assess clarity, confidence, effort, and perceived ease. Ask focused questions tied to the journey, such as whether the patient knew what to do next or whether the instructions were easy to follow. Keep feedback requests brief and accessible, and make sure the team can act on what it learns.
Use a balanced set of diagnostics rather than one headline number. A primary measure shows whether the intended outcome moved, while a balancing measure checks whether the change created new problems, such as shifting calls to another department, increasing staff overtime, or worsening access for a group that uses a different channel. Segment results where possible, while protecting privacy and avoiding conclusions from very small samples. Compare the test period with a baseline and account for ordinary variation, seasonal demand, and operational changes. Report both what improved and what remains uncertain.
Set expectations for how the team will interpret results before the test begins. Define the period, population, and comparison point, then agree on what would count as a promising signal, a negative signal, or an inconclusive result. Small tests may not establish statistical certainty, but they can still reveal implementation problems, patient confusion, or a reason to run a better test. Avoid declaring victory based on one unusually good day or one anecdote that supports a preferred idea. The purpose of measurement is to support a thoughtful next decision, not to make every experiment look successful.
A common misconception is that every patient wants the fastest, most digital, and most automated path possible. Speed and convenience matter, but patient experience also depends on choice, reassurance, accessibility, and the ability to reach a person when a situation requires judgment. A portal can be an excellent option for one patient and a new barrier for another, while a phone call can feel reassuring to one person and frustrating to someone who cannot call during business hours. Do not confuse an organization’s preferred channel with the patient’s preferred or practical channel. Design for a workable set of options and make the purpose of each one clear.
Another pitfall is treating the map as a one-time workshop deliverable. A colorful diagram can create energy, but it will not improve access unless someone owns the next action, has the authority to test it, and returns to the evidence. Assign an owner to each priority and set a review date before the group leaves the room. Keep the map available as a living reference, updating it when policies, systems, staffing, or patient needs change. The tool should help teams coordinate decisions, not become a presentation that is admired and forgotten.
Be careful not to let internal assumptions masquerade as patient insight. Staff expertise is essential, but statements such as “patients do not read the message” or “everyone knows how referrals work” are hypotheses until evidence supports them. Similarly, a low complaint count does not prove that a process is easy; people may abandon the task, choose another provider, or decide that raising a concern is not worth the effort. Look for silent signals such as incomplete forms, repeat contacts, missed steps, and sudden drop-offs. Ask what the available evidence cannot show, then find a practical way to learn more.
Finally, avoid fixing the most visible symptom while leaving the underlying cause untouched. Adding another reminder may not solve confusion created by inconsistent instructions, and adding a phone line may not help if the team cannot resolve the issue once a patient reaches someone. Check whether a proposed solution addresses the barrier in the journey or merely moves the work to a different channel or department. Consider how the change affects patients with different needs, as well as the staff responsible for delivering it. A good improvement reduces avoidable effort without creating a new obstacle somewhere else.
Once a test shows promise, decide how to make the change reliable. Document the new step in the place staff actually use, whether that is a scheduling guide, a call script, an electronic workflow, or a patient communication template. Make ownership clear so that the process does not depend on one enthusiastic employee remembering an informal workaround. Brief the people who will deliver the change, explain why it matters to patients, and invite them to identify practical concerns before expansion. A process is only an improvement if it works consistently in real conditions.
Continue listening after implementation because patient needs and operating conditions shift. Review the chosen KPI on a regular cadence, gather frontline observations, and watch for signs that the improvement is no longer working as intended. If a measure worsens, investigate rather than blame the team or the patient; the new process may be unclear, capacity may have changed, or another system may be interfering. If results improve, verify that the benefit holds across relevant groups and channels before extending the change. Sustained patient experience improvement comes from learning cycles, not from assuming that one successful test lasts forever.
Build a modest routine that makes the work manageable. A monthly review of one journey, one friction point, and one test can be more effective than an ambitious annual mapping project that never returns to implementation. Share useful findings with clinical, operational, and marketing teams so that patient-facing messages match what the service can actually deliver. Keep a short record of the problem, the evidence, the change, the measures, and the decision. Over time, these records help the organization see recurring causes, avoid repeating failed experiments, and make patient journey mapping a practical management habit.
You do not need a complete redesign to make a meaningful difference. Choose one moment when patients hesitate, repeat themselves, wait without clarity, or abandon the next step, then trace what happens immediately before and after it. Ask patients and frontline colleagues what they are trying to accomplish and what makes it difficult. Use the map and checklist to separate the most important problem from the first solution that comes to mind. A focused investigation can turn a vague concern about patient experience into a specific, testable opportunity.
Bring the right people together for a short working session and leave with a named owner, a small change, and a way to tell whether it helped. Protect time for patient input, check safety and accessibility, and choose both an outcome measure and a balancing measure. If the first test does not work, treat the result as useful information about the process rather than a reason to abandon improvement. When it does work, share the learning and decide how to make the change dependable for more patients. The most effective patient journey work is practical, shared, and grounded in what people actually experience.
Make care easier to find, start, and continue. If your team is ready to identify where patients get stuck and turn those insights into clear next steps, start with one journey this week. Bring your map, your questions, and the point of friction you want to solve, and let’s explore a practical path forward together. Contact us to discuss how a focused patient journey review can help your organization improve healthcare access and create a more navigable patient experience.